Dog Bone Cancer Symptoms: Radiographic Clues and Early Detection of Osteosarcoma in Dogs
Dog bone cancer symptoms in dogs often start with progressive lameness, pain, swelling, and poor response to NSAIDs. Learn how osteosarcoma appears on radiographs, which dogs are most at risk, and why three-view thoracic staging is essential for accurate diagnosis and referral planning.

Dog Bone Cancer Symptoms
Introduction
A primary bone tumor often presents with non-specific signs of lameness or swelling. While this may be identified on radiographs at the initial visit, at times, medical management is attempted and the failure to improve is an indicator that further diagnostics are necessary.
Osteosarcoma, or OSA, is the most common primary bone tumor in dogs and accounts for about 85% of primary skeletal malignancies. It is an aggressive disease with a strong tendency to metastasize, most often to the lungs.
Early recognition is paramount to timely treatment. . Recognizing the right signalment, identifying aggressive radiographic changes, and completing proper staging can move a case from vague lameness to timely diagnosis, referral, and treatment planning.
This article reviews the radiographic features that should raise concern for osteosarcoma, the key differentials, and the staging steps that should follow.
What is the most common presentation for canine primary bone tumors??


The earliest bone cancer symptoms can be subtle, and that is part of what makes osteosarcoma easy to miss at first. Many dogs are initially treated for a sprain, arthritis flare, or soft tissue injury before imaging reveals a much more serious process.
Common symptoms include:
- Progressive lameness
- Localized limb pain
- Firm swelling over the affected bone
- Poor or short-lived response to NSAIDs
- Reluctance to exercise, jump, or bear weight
- Behavioral changes caused by pain
- Pathologic fracture in advanced cases
Pain is one of the defining features. Some dogs improve briefly on anti-inflammatory medication, only to worsen again as the tumor continues to destroy bone. Owners may notice that the limp is becoming more consistent, that the dog no longer wants to walk or play, or that a previously active dog is suddenly quiet and withdrawn.
A high-risk dog with worsening lameness over days to weeks, especially when NSAIDs are not giving lasting relief, should prompt imaging.
Which dogs are most at risk for osteosarcoma?
Signalment is one of the most useful early clues.
Osteosarcoma is most common in large and giant breed dogs, usually those weighing more than 40 kg. Breeds frequently associated with OSA include:
- Rottweiler
- Great Dane
- Irish Wolfhound
- Greyhound
- Doberman Pinscher
- German Shepherd Dog
- Golden Retriever
There is a bimodal distribution of age with most affected dogs middle-aged to older, with a common age range of about 7 to 10 years. There is also a smaller peak in younger, rapidly growing large-breed dogs.
When this signalment overlaps with persistent lameness and focal limb pain, radiographs should be performed.
Where does osteosarcoma usually occur in dogs?
About 80% of canine osteosarcomas occur in the appendicular skeleton. A practical rule many clinicians use is:
Away from the elbow, toward the knee.
That pattern helps explain why the most common sites are:
- Distal radius
- Proximal humerus
- Distal femur
- Proximal tibia
The distal radius is the single most common appendicular location.
The remaining 20% occur in the axial skeleton, including the:
- Skull
- Ribs
- Vertebrae
- Pelvis
Axial osteosarcoma can be harder to recognize early because the signs are often less specific. A dog with rib, vertebral, or pelvic involvement may present with discomfort, swelling, neurologic signs, or vague mobility changes rather than a classic single-limb lameness history.
What osteosarcoma looks like on radiographs

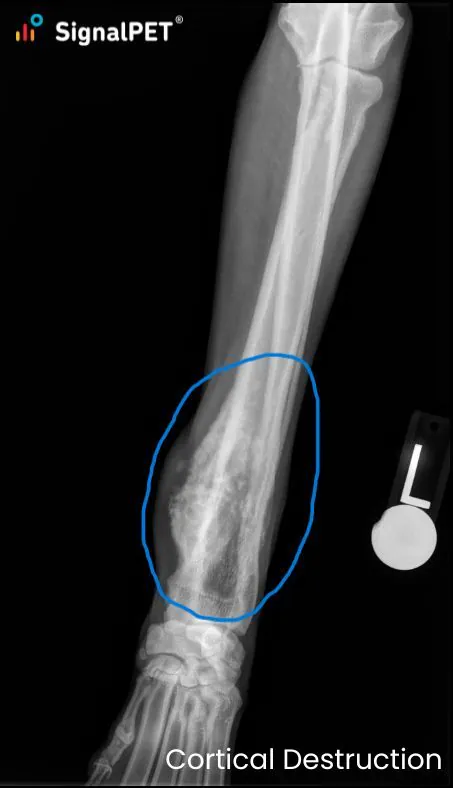
Radiography is usually the first imaging step to rule out bone cancer.. In many cases, the radiographs are what shift the case from non-specific orthopedic pain to suspected malignant neoplasia.
Key radiographic features of osteosarcoma
A classic osteosarcoma lesion often shows a mixed lytic and productive appearance. In simple terms, there is both bone destruction and abnormal new bone formation.
Important features of aggression to look for include:
- Wide zone of transition
- Cortical destruction
- Irregular periosteal reaction
- Moth eaten or permeative lysis
- Possible pathologic fracture
Wide zone of transition
One of the strongest radiographic clues to malignancy is a wide zone of transition. Instead of a sharply defined lesion, there is a gradual and aggressive transition between normal and abnormal bone. That lack of a clean margin suggests a destructive process.
Cortical destruction
As the tumor progresses, the cortex loses its normal structure and continuity. Cortical destruction reflects loss of bone integrity and is one reason these lesions are painful and at risk for fracture.
Periosteal reactions
Aggressive periosteal reactions are common in osteosarcoma and may include:
- Codman’s triangle
- Sunburst pattern
- Amorphous or irregular periosteal new bone
These patterns are not specific to osteosarcoma alone, but they are instead indicative of an aggressive lesion in general.
Moth-eaten or permeative lysis
As compared to a bone cyst, which has geographic lysis, malignant lesions tend to have smaller regions of variably-sized lysis.
Can radiographs confirm osteosarcoma?
No. At best, radiographs can tell you that an aggressive, rather than benign, process is occuring..
This is a critical point for both GPs and owners. Imaging can tell you that the lesion is aggressive and highly suspicious for a malignant bone process, but definitive diagnosis still requires tissue sampling, usually by cytology or histopathology.
That distinction matters because several different diseases can mimic osteosarcoma radiographically.
Differential diagnoses for aggressive bone lesions in dogs
- An aggressive bone lesion can be broken down into two broad categories of differentials, malignant neoplasia and osteomyelitis. Malignancy can further be broken down into other types of primary osseous neoplasia, round cell neoplasia, or metastatic neoplasia.
Chondrosarcoma, and other types of primary bony neoplasia, can be indistinguishable from osteosarcoma. Metastatic disease may produce multiple skeletal lesions, especially in dogs with a known primary tumor. Multiple myeloma often creates more uniform “punch out” lytic lesions and may have a different overall distribution.
Infectious disease is particularly important not to overlook. Fungal osteomyelitis can look very similar to osteosarcoma on radiographs, depending on the patient’s geography and exposure history. Bacterialosteomyelitis may also create aggressive bone change, though the clinical context often differs.
Because of this overlap, treatment decisions should not rely on radiographs alone when a sample can be obtained safely.
Why thoracic staging is mandatory in suspected osteosarcoma


Once a primary bone tumor is suspected, staging is not optional. It is a core part of the diagnostic workup.
Osteosarcoma has a strong metastatic preference for the lungs. That means every suspected case should be evaluated for thoracic spread before definitive treatment planning.

Three-view thoracic radiographs
A minimum thoracic staging study should include three views:
- Right lateral
- Left lateral
- Ventrodorsal or dorsoventral
Using all three projections improves pulmonary nodule detection. Lesions can be obscured on one view and become more obvious on another because of changes in overlap and positioning.
When reviewing the chest, look carefully for:
- Pulmonary nodules
- Mediastinal or sternal lymphadenopathy
- Metastatic lesions in the ribs or spine
Even when no metastases are visible, it is important to communicate that radiographs do not rule out microscopic or very small metastatic disease. In some cases, referral for CT may be useful to increase sensitivity for metastasis.
From suspicion to referral
When the signalment, clinical picture, and limb radiographs all suggest osteosarcoma, the next step is not watchful waiting. Fine needle aspiration is critical for a definitive diagnosis and proper staging can be performed including thoracic radiographs, routine bloodwork, and potentially abdominal ultrasound.
Treatment and prognosis
Management of osteosarcoma in dogs is centered on two realities: the primary lesion is painful and locally destructive, and metastatic disease is usually assumed to be present even when it is not yet visible.Discussion with the client is warranted on if the goals are treatment of palliation of pain. Treatment options, including surgery, radiation, and chemotherapy are constantly evolving and discussion with an oncologist is warranted to assess what can be done in general practice and what would necessitate referral. Having a proper diagnosis is key to furthering these discussions.

Most patients never get a second opinion. Yours can.

A practical note on pain control
Pain management should start early. Dogs with osteosarcoma are often significantly more uncomfortable than they appear on physical exam.
A dog with suspected bone cancer symptoms should not be left under-medicated while waiting for referral. Starting appropriate analgesia improves welfare immediately and helps stabilize the patient during the diagnostic process.
AI-assisted thoracic review in staging
Consistent review of three-view thoracic radiographs can be challenging, especially when pulmonary nodules are small or subtle.
SignalPET AI can support more consistent three-view thoracic interpretation in general practice and help flag pulmonary findings that may justify closer review or CT staging. It should not replace clinician judgment, but it can support a more standardized approach to metastatic screening.
Practical takeaways for GPs and informed owners
Osteosarcoma is often first suspected in general practice. That makes early recognition one of the most important opportunities to improve case flow and patient welfare.
The most useful pattern to remember is this: a large or giant breed dog, typically middle-aged to older, presents with progressive lameness, focal pain, poor response to NSAIDs, and aggressive bone change on radiographs.
At that point:
- Treat pain early
- Do not assume the lesion is confirmed osteosarcoma based on imaging alone
- Stage the chest with three-view thoracic radiographs
- Consider CT when staging accuracy will change decisions
- Discuss treatment options
The goal is not just faster diagnosis. It is better decision-making, less suffering, and clearer options for the owner.
Conclusion
Dog bone cancer symptoms can look deceptively ordinary at first. A limp that lingers, pain that keeps worsening, or swelling over a limb may be the earliest signs of osteosarcoma in dogs.
That is why radiographs matter, and why interpreting them correctly matters just as much. A wide zone of transition, cortical destruction, aggressive periosteal reaction, and soft tissue swelling should immediately raise concern for a malignant bone lesion, especially in a large-breed dog in the right age range.
Still, imaging is only one step. Radiographs suggest malignancy, they do not confirm osteosarcoma. Proper sampling, complete thoracic staging, and timely referral are what turn suspicion into a real plan.
For GPs, this is one of the most important practical points: do not wait too long to investigate persistent dog bone cancer symptoms. Earlier imaging, earlier staging, and earlier referral can make a meaningful difference in both quality of life and treatment options.
Radiographs are especially helpful when the clinical presentation is not straightforward. A painful dog with fever, multifocal discomfort, or marked vertebral endplate change may have diskospondylitis rather than IVDD. In that setting, radiographs can redirect the whole workup.
may be more useful if trauma is suspected as it can be done rapidly and answer additional questions.
FAQs
The earliest signs are usually progressive lameness, localized pain, swelling over a bone, and poor response to NSAIDs. In advanced cases, a pathologic fracture may occur.
Osteosarcoma often appears as an aggressive bone lesion with a wide zone of transition, cortical destruction, periosteal reaction, soft tissue swelling, and a mixed lytic and productive pattern.
No. Radiographs can strongly suggest a malignant bone lesion, but definitive diagnosis requires cytology or histopathology.
It most commonly affects the appendicular skeleton, especially the distal radius, proximal humerus, distal femur, and proximal tibia. A useful rule is away from the elbow, toward the knee.
Thoracic radiographs are used to stage the lungs for metastatic disease. Three-view thoracic imaging is recommended because pulmonary nodules may only be visible on one projection.
Files Gallery


Table of Contents


Book a Demo
Most patients never get a second opinion. Yours can.
SignalPET helps you bring real diagnostic support to the cases that would otherwise get no second opinion, with three layers of clinical support